
What causes children to snore? What symptoms warrant a medical examination and treatment?
Last updated:

It's normal for children to snore. Sometimes they only snore when they have a cold or nasal congestion. However, if your child snores frequently, loudly, has difficulty breathing, gasps for breath, or is unusually sleepy, hyperactive, or irritable during the day, you should take them to a doctor for evaluation.
Not all children who snore have obstructive sleep apnea (OSA). However, if snoring is frequent or accompanied by other symptoms, it's worth paying attention. The following information will help parents monitor their child's symptoms at home more easily, understand the different tests available, and know which treatment is most appropriate for each child.[1]
What is the difference between normal snoring and OSA (Obstructive Snoring)?
Snoring is caused by narrowing of the upper airway during sleep. The tissues in the throat or soft palate vibrate and produce sound. Some children snore occasionally without significant obstruction, but others may have difficulty breathing during sleep, ranging from mild to obstructive sleep apnea (OSA).
OSA (Obstructive Sleep Apnea) is a condition where the upper airway repeatedly narrows or closes during sleep, resulting in incomplete breathing and poor sleep quality. Snoring can provide clues for further observation, but snoring alone cannot confirm OSA or indicate its severity. History, symptoms, questionnaires, video evidence, or tonsil size alone are not sufficient to replace a medical evaluation for diagnosis.[3]
When observing your child, don't just focus on whether they snore. Also, consider how often they snore, whether they breathe heavily, whether there are periods where they seem to pause and gasp for breath, and whether their behavior or alertness changes during the day.
If a child has OSA (Obstructive Sleep Apnea) and does not receive care, they may experience insufficient sleep, which can affect their behavior, learning, growth, or heart health.[6] However, snoring alone doesn't mean everyone has these symptoms. Therefore, doctors need to help differentiate general snoring from OSA and look for other possible causes.
What causes a child to snore?
Children can snore for many reasons, and some people have several factors at once. Common causes include:
Enlarged tonsils or adenoids
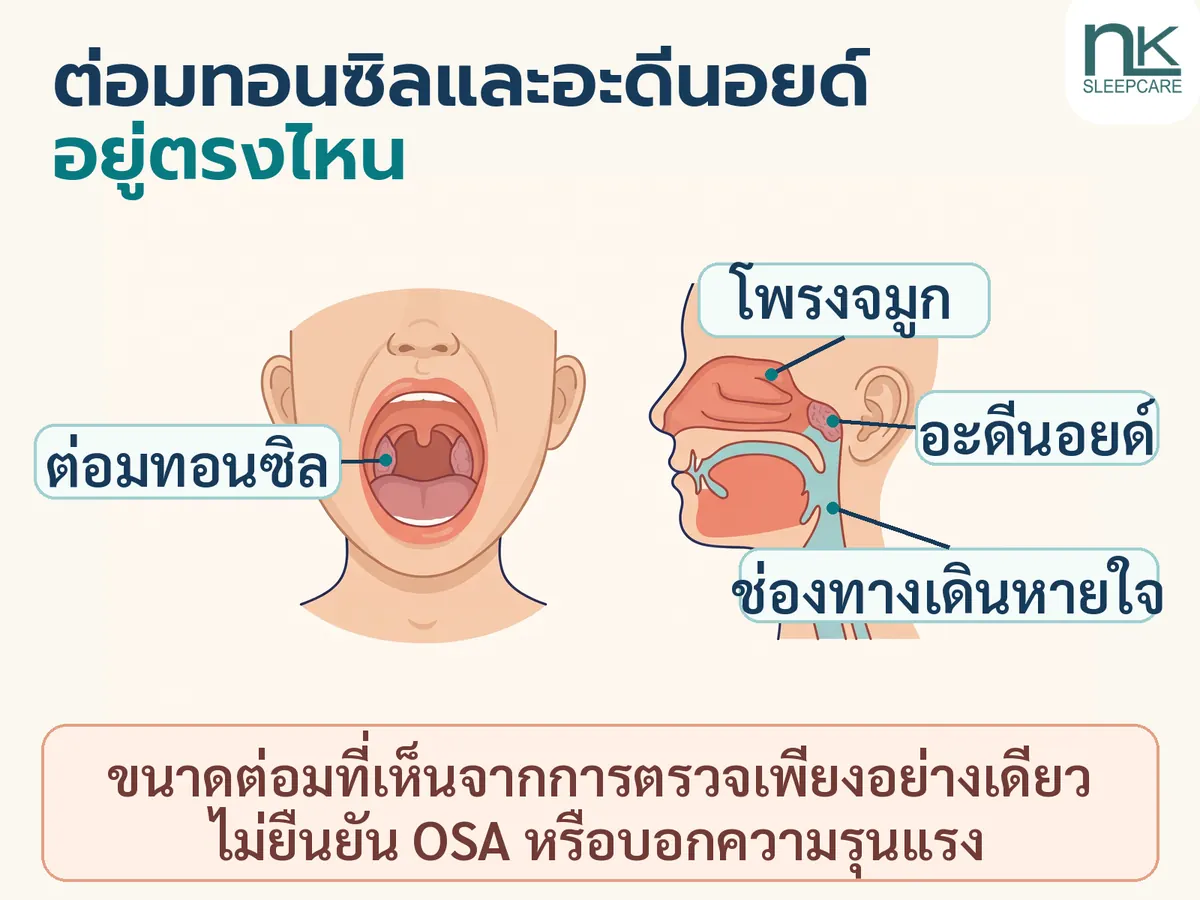
The tonsils are located on either side of the throat, while the adenoids are located behind the nasal cavity.[6] When these tissues grow, the airway may narrow, especially during sleep. However, the size of the glands visible on examination alone is not enough to confirm whether a child has OSA or how severe the condition is.[3]
Nasal congestion or allergies.
Nasal congestion, rhinitis, allergies, or respiratory infections can cause children to breathe through their mouths and snore more. If this only occurs during a cold, the symptoms may improve once the illness is gone. However, if nasal congestion or snoring persists, it's best to consult a doctor to determine the cause, rather than self-medicating or continuing to use over-the-counter drugs.[1]
Overweight or obesity.
Being overweight or obese increases the risk of obstructive sleep apnea in some children. Weight management should be age-appropriate and done in collaboration with a healthcare team; one should not wait for weight loss before diagnosing or treating sleep breathing problems.[1]
Facial structure, oral cavity, or airway.
Certain parts of the jaw, tongue, palate, or facial structure can narrow the airway. Therefore, some children require a multidisciplinary team of doctors to determine the exact location of the obstruction and the appropriate treatment.[1,7]
Certain comorbidities or specific conditions.
If a child has Down syndrome, craniofacial abnormalities, neuromuscular disorders, complex comorbidities, or is under 1 year of age, the doctor must assess each child individually based on age and comorbidities. Recommendations for uncomplicated OSA should not replace a comprehensive medical evaluation.[1,3,7]
What symptoms should you watch out for?
OSA symptoms in children may differ from adults. Some may not be noticeably sleepy, but instead become more restless, have decreased concentration, or become easily irritable. Observe your child both during the day and at night and describe your symptoms to your doctor; this will help provide a more complete picture.[6,7]
Symptoms that can be observed at night.
- Frequent or loud snoring.
- It was like my breath stopped for a moment, then I suddenly jolted.
- You have to exert effort to breathe, to the point that your chest or neck sinks in while you breathe.
- Breathing through your mouth, dry throat, or waking up frequently to drink water.
- Restless sleep, excessive sweating, or frequently tilting the head back.
- Bedwetting, especially if it recurs after a period of recovery.[1,6,7]
If you see these symptoms, you should take your child to a doctor for evaluation. However, one symptom alone is not enough to diagnose OSA, nor can it indicate its severity.
Symptoms that may be visible during the daytime.
- Difficulty waking up, feeling sleepy during the day, or accidentally falling asleep at an inappropriate time.
- Becoming more mischievous, easily irritated, experiencing mood swings, or having difficulty controlling their behavior.
- Concentration, memory, or academic performance change.
- Headache or dry mouth in the morning.
- Abnormal growth or weight.[6,7]
Daytime symptoms can be caused by many factors, so don't conclude that a child has OSA based solely on behavior or academic performance. Other causes should also be considered.
Things to write down before taking your child to the doctor.
Before taking your child to the doctor, try writing down their symptoms, as many things happen while they're sleeping. Here's what you might notice:
- How many nights a week does your child snore, and how long has this been going on?
- Do you snore loudly all the time, or only when you have a cold or allergy symptoms?
- Does she have difficulty breathing, gasp, her chest sinks in, or exhibit any unusual sleeping positions?
- How do your behavior, concentration, or learning change when you feel sleepy during the day?
- Do you have allergies, are you taking any medication, have your weight changed, have any underlying medical conditions, or have you received any previous treatments?
If it's safe and won't disturb your child, you can record a short video showing their breathing patterns and chest movements. This clip can help your doctor understand what's happening at home, but it can't confirm OSA or replace a sleep study.[3]
When should you take a child who snores to see a doctor?
You should schedule a doctor's appointment for your child if they snore frequently along with any of the following symptoms: interrupted breathing, gasping for breath, labored breathing, excessive mouth breathing, restless sleep, or daytime changes in behavior, concentration, alertness, or growth.[1] Even if you're unsure whether your child is snoring, you should consult a doctor if you notice any of these worrisome symptoms.[6]
If a child has obesity, Down syndrome, craniofacial abnormalities, or neuromuscular disorders, the doctor will consider any co-existing conditions, as these children may require a different approach than typical children.[4,7] For children who have already received treatment but continue to snore or experience a recurrence, they should return for reassessment by the treatment team. It is not advisable to conclude that the treatment is ineffective or to leave the condition untreated.[1,5]
Emergencies that shouldn't wait.
If a child stops breathing, has severe difficulty breathing, or their lips or skin turn bluish, gray, or unusually pale, seek emergency medical help immediately.⁹¹⁰¹¹
What tests will the doctor perform?
The doctor will begin by asking about symptoms at home, then examine the nose, mouth, tonsils, breathing, facial structure, growth, and comorbidities. Some children may need to see a pediatrician, sleep specialist, ENT specialist, or a multidisciplinary medical team.
Taking a medical history and performing a physical examination is very helpful, but it's not always accurate in differentiating general snoring from OSA (Obstructive Snoring) or determining its severity.[1,3] If a doctor suspects OSA (Obstructive Sleep Apnea), they often consider a polysomnography (PSG) sleep study. However, if access to a PSG is unavailable, the doctor may choose another appropriate test or refer the patient to a specialist.[1,3]
What is PSG?
PSG is a sleep study that monitors sleep throughout the night. The team records breathing, airflow, chest movement, oxygen levels, pulse, and sleep stages. This data helps doctors determine if there is any obstruction, how severe it is, and how to manage it.
The American Academy of Sleep Medicine (AASM) states that overnight PSG (Sleep Monitoring) in a staffed laboratory is the standard for diagnosing OSA (Obstructive Sleep Apnea) in children and may be used in some cases, such as to adjust pressure during positive pressure therapy (PAP) and to monitor outcomes in certain children after treatment.[3]
Can the Home Sleep Apnea Test (HSAT) be used as a substitute for PSG in children?
The AASM (American Academy of Medicines and Sciences) states that it does not recommend the use of home sleep apnea tests (HSAT) to diagnose OSA in children under 18 years of age because there is insufficient research evidence to confirm its effectiveness in children.[2]
You should not self-medicate or choose tests based on advertisements. If you suspect OSA, have a doctor evaluate your child and choose the appropriate testing method. For diagnosing OSA in children, the guidelines referenced in this article use overnight PSG (Postpartum Grafting).[1,3]
What are the treatment options?
There's no one-size-fits-all treatment. The doctor will assess whether it's just snoring or also obstructive sleep apnea (OSA), where the obstruction is, the severity of the symptoms, the child's age, and any co-existing conditions, then choose the most appropriate treatment for each child.[1,4,5]
If there are co-existing conditions, the doctor may prescribe medication based on the cause, but the doctor must determine the type of medication, duration, and monitoring. There is no one-size-fits-all medication, and you should not self-medicate with antibiotics, allergy medication, or other drugs to treat OSA.[1]
The following examples illustrate some of the things a doctor might consider; it's not a list of options to choose from.
Manage nasal conditions, comorbidities, and weight.
Avoid secondhand smoke.[7] Manage nasal congestion or allergies as directed by your doctor. If you are overweight or obese, manage your weight in collaboration with your healthcare team. Weight management is supplementary and should not delay necessary OSA testing or treatment.[1]
Tonsillectomy and adenoidectomy
If OSA (obstructive sleep apnea) is detected along with enlarged tonsils or adenoids, the doctor may consider surgery if deemed appropriate. Some children may retain OSA after surgery.[4,5]
CPAP is for some children.
Some children may benefit from a continuous positive airway pressure (CPAP) machine. An experienced team will help select a mask, set the pressure, and monitor progress. You should not buy the machine or adjust the pressure yourself.[1,3,5]
If your child still snores after treatment, what should you do?
If, after treatment, your child continues to snore, has difficulty breathing, or exhibits daytime symptoms such as difficulty waking up, excessive sleepiness, increased restlessness or irritability, decreased concentration, or changes in academic performance, do not conclude that the treatment is ineffective or ignore it. You should discuss these symptoms with the treatment team to determine what further monitoring or testing is needed.[1,6,7]
The medical team may review symptoms, previous test results, current treatments, risk factors, and potential locations of obstructions. If your child is taking medication or a device, they may also review how consistently they are using it as planned.[3,5] The doctor will then choose what kind of follow-up or additional testing is most suitable for that child, which may include sleep studies.[1] You should not adjust the medication, device, or pressure yourself.[1]
If symptoms persist or return after surgery, please see the section "What to do if symptoms persist after surgery" below, which provides specific advice for your case.
Frequently asked questions about children snoring.
Is it normal for children to snore?
Children may snore occasionally when they have a cold or nasal congestion, but if the snoring is frequent, loud, interrupted, labored, or occurs during the day, they should be evaluated by a doctor. Don't wait for it to go away on its own as they grow older.[6]
Do all children who snore have OSA (Obstructive Sleep Apnea)?
No, snoring is just a signal to observe further. It doesn't confirm OSA (Obstructive Shock Absorption) in the child. Diagnosis requires a history, physical examination, and other tests deemed appropriate by the doctor.[1,3]
Can video recording a baby sleeping help doctors?
Short video clips showing breathing patterns, chest movement, and suspected periods of difficulty breathing may help doctors understand what is happening at home, but these clips do not indicate severity and cannot replace a polysomnography (PSG) sleep study.[3]
Can I get a test at home instead of at PSG?
The AASM states that the Home Sleep Apnea Test (HSAT) is not recommended for diagnosing OSA in children under 18 years of age.[2] The doctor will choose the testing method based on the child's age, risk factors, and the availability of the medical facility or the team caring for the child.[1,3]
Does everyone recover after surgery?
No, tonsillectomy and adenoidectomy are only suitable for children, but OSA (Obstructive Sensitive Arthritis) may persist or recur, so monitoring and follow-up examinations are necessary when deemed appropriate by a doctor.[4,5]
Can children use CPAP?
Some children can use continuous positive airway pressure (CPAP) machines, such as those who are not suitable for surgery or who still have obstructive sleep apnea (OSA) after surgery. However, an experienced pediatric team must help select the mask, set the pressure, and monitor the results.[1,5]
What should I do if my symptoms persist after surgery?
If your child continues to have OSA (Obstructive Shock Absorption) after tonsil and adenoid surgery, contact the medical team for continued care, as some children may develop OSA after surgery.[5] The doctor will review the symptoms, risk factors, and appropriate test results, and may consider repeating the sleep study.[3,5] If obstructive spontaneity (OSA) is confirmed or suspected, the treatment team will select a care method based on the cause and suitability for each child. This may include the use of CPAP or further assessment of the obstruction location.[5] You should not buy devices or change treatments on your own.[5]
In summary: What should you do if your child snores?
Not all children who snore have OSA (Obstructive Sleep Apnea). However, if they snore frequently, have interrupted breathing, labored breathing, or exhibit changes in behavior and alertness during the day, they should be evaluated by a doctor. If the doctor suspects OSA, they will usually consider performing a nighttime PSG (Phase Gait Gaiterometry).[1,3] And HSAT is not recommended for diagnosing OSA in children.[2]
Treatment may begin with managing factors that worsen symptoms, treating allergies, surgery, or using CPAP, depending on the cause and suitability.[1,4,5] Children who still experience symptoms after treatment should return for follow-up with the treatment team. Do not adjust medication, equipment, or pressure yourself.[1,5]
If you're looking for a medical facility for a sleep study, ask beforehand if they have a team and testing systems for children, as each facility offers different services.
This content provides general information and does not replace a medical diagnosis or advice. If you suspect your child has sleep apnea, consult a pediatrician, sleep specialist, or ENT doctor.
References
- American Academy of Pediatrics (AAP), 2012: Diagnosis and Management of Childhood Obstructive Sleep Apnea Syndrome. – The 2012 guidelines are intended for historical reference and should not automatically be interpreted as representing current guidelines. Official AAP full text
- American Academy of Sleep Medicine: Home Sleep Apnea Test for the Diagnosis of OSA in Children
- American Academy of Sleep Medicine: Respiratory Indications for Polysomnography in Children
- AAO-HNSF: Tonsillectomy in Children – Updated Guideline
- American Thoracic Society: Persistent Post-adenotonsillectomy OSA in Children
- American Academy of Pediatrics – HealthyChildren.org: Sleep Apnea in Children
- National Heart, Lung, and Blood Institute: Sleep Apnea in Children
- National Cancer Institute: Anatomy of the throat
- American Academy of Pediatrics – HealthyChildren.org: When Your Child Needs Emergency Medical Services
- American Academy of Pediatrics – HealthyChildren.org: When to Call Emergency Medical Services (EMS) for Your Child
- healthdirect Australia: Symptoms of serious illness in babies and children


